Google Research AI dates pregnancies from novice-run blind sweep ultrasound
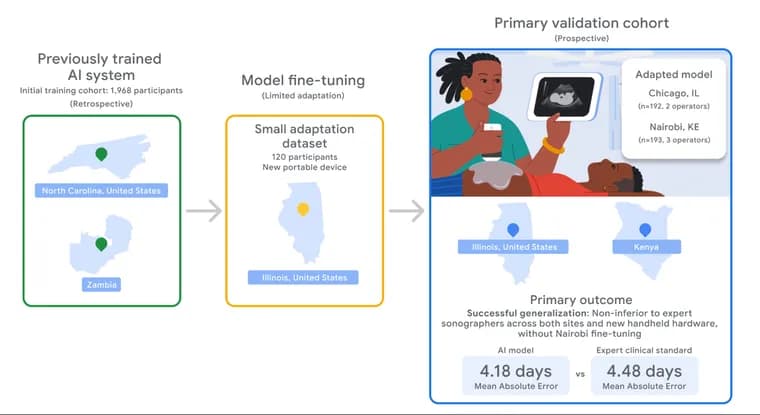
Google Research has published a blog post, dated October 21, 2026 and written by Angelica Willis (Research Engineer, Google Research) and Nichole Young-Lin (Clinical Lead, Google for Health), about a prospective multi-center study. The paper, "Generalization of AI-Based Gestational Age Assessment Using Blind Sweep Ultrasonography", appears in JAMA Network Open. Its claim: AI-based interpretation of blind sweep ultrasound can let operators without sonography training, using low-cost portable probes, produce gestational age assessments the authors describe as expert-level.
The motivation is access. The post cites a WHO estimate of more than 250,000 preventable deaths worldwide each year from pregnancy-related complications, and says two-thirds of people globally lack access to diagnostic imaging such as ultrasound. Many people in low-resource settings go through an entire pregnancy without a single scan. Traditional sonographer training is expensive and takes a multi-year commitment. A blind sweep avoids that: a frontline health worker glides a portable probe across the abdomen in a standardized pattern, and machine learning interprets the images. Gestational age, meaning how far along the pregnancy is, matters because screening, treatments and decisions about delivery all hang on that timeline, as a passage quoted in the post puts it.
What is new is the setting. The authors' earlier work validated the model on unseen patients from the same retrospective cohort it learned from. This study ran the system live on mobile devices in real clinics, with only novice operators, unfamiliar ultrasound equipment and minimal fine-tuning.
The original model was trained on ultrasound data from North Carolina and Zambia, collected with Sonosite, GE and Butterfly Networks commercial probes. For the study it was paired with the Clarius C3, a commercial handheld transabdominal probe. The sites differed in when women first come for prenatal care, how many routine ultrasounds they get, and how gestational age is usually dated. The model was minimally tuned on only one target population: a pilot set of 120 participants from Chicago, about 6% of the original training set. That tuning adapted it to the new probe hardware and extended its gestational age prediction range beyond 36 weeks. No data from the Nairobi site was used for fine-tuning, so the Kenyan validation stayed a strictly independent, external test. The study also included multiple gestation pregnancies, which can be hard to track and measure for both people and software.
The AI's estimates from blind sweeps were compared with formula-based estimation from the clinical standard, in which an expert sonographer finds several specific cross-sections of the fetus to take precise biometry measurements, a task the post calls hard to scale, years in the training and highly operator-dependent. The primary cohort was 385 participants between 16 and 36 weeks of pregnancy. The authors conclude that the AI estimate of fetal age had accuracy comparable to the current standard of care from expert operators and more expensive, traditional cart-based ultrasound machines. In exploratory metrics, for fetal weight extremes above the 90th percentile, the model outperformed traditional biometry formulas, which the authors present as robustness to variation in fetal size.
The deployment also produced practical lessons. Swappable batteries mattered more than plug-in docking stations for keeping devices charged between consecutive patients. The authors add that deploying such systems will require building deep trust with clinicians and patients, and suggest safeguards in the app, such as model confidence estimates that reject poor-quality sweeps and convey uncertainty to the clinician.
The post frames the result as showing potential to expand prenatal coverage for millions in under-resourced areas by empowering minimally trained community health workers, and says the insights feed Google's next-generation multimodal medical intelligence research. Co-authors come from Google Research, Jacaranda Health and Northwestern University Feinberg School of Medicine.
Key facts
- A prospective multi-center study in JAMA Network Open tested an AI model that estimates gestational age from blind sweep ultrasound taken by novice operators with a low-cost handheld probe (Clarius C3).
- The primary cohort had 385 participants between 16 and 36 weeks of pregnancy; the authors report accuracy comparable to expert operators using more expensive cart-based machines.
- The model was trained on data from North Carolina and Zambia, then fine-tuned on only 120 Chicago participants (about 6% of the original training set); no Nairobi data was used, keeping the Kenyan test independent.
- In exploratory metrics, for fetal weight above the 90th percentile, the model outperformed traditional biometry formulas.
- Field lessons: swappable batteries beat plug-in docking stations, and confidence estimates that reject poor sweeps are proposed as a trust safeguard.
Why it matters
The post cites a WHO estimate of more than 250,000 preventable deaths a year from pregnancy-related complications, and says two-thirds of people globally lack access to imaging like ultrasound. Prenatal ultrasound depends on scarce, expensive sonographer training. If trained AI can read standardized sweeps from minimally trained workers, scanning could reach places that now go without a single scan in pregnancy. The step forward here is the test design: earlier work validated the model on unseen patients from the same retrospective cohort it learned from, while this study ran it live in real clinics, on new hardware, with novice operators.
Who it affects
Frontline and community health workers in low-resource settings, who would perform the scans without specialized sonography training. Pregnant women in under-resourced areas, who are the intended beneficiaries. Clinicians who would receive the AI's estimate and its uncertainty signals. The work involved co-authors from Google Research, Jacaranda Health and Northwestern University Feinberg School of Medicine, with sites including Chicago and Nairobi.
How to use it
This is research, not a product. The post names no product, launch or deployment timeline. The described workflow is a health worker gliding a low-cost handheld probe (the study used the Clarius C3) across the abdomen in a standardized pattern while the AI runs on a mobile device. For anyone building similar systems, the authors flag two practical points: swappable batteries matter more than plug-in docking stations when patients are scanned back to back, and in-app confidence estimates can reject poor-quality sweeps and show uncertainty to the clinician.
How solid is it
The evidence is a prospective, multi-center study published in JAMA Network Open, which is stronger than the earlier same-cohort retrospective validation. The Nairobi site was kept fully out of fine-tuning, so that part works as an independent external test. The primary cohort was 385 participants. The accuracy claim (comparable to expert biometry on cart-based machines) comes from the authors' own post, and this retelling carries no error figures. The fetal weight result is labelled exploratory. The quoted passage about gestational age is not attributed to a named speaker.
Risks and caveats
The authors speak of potential: the tool has the potential to increase availability of ultrasound-based pregnancy assessment, and the research demonstrates the potential to expand prenatal coverage. Improved outcomes are not demonstrated here. The cohort covers 16 to 36 weeks; the fine-tuning extended the prediction range beyond 36 weeks, but the primary evaluation is within that window. The model still needed a small amount of local fine-tuning (120 participants) to adapt to new probe hardware. The authors themselves note that real deployment needs deep trust from clinicians and patients, and that safeguards for poor-quality scans and model uncertainty are needed. No regulatory approval is mentioned.
“The gestational age is basically how far along a woman is in pregnancy. All of our screening, a lot of our treatments, a lot of our indications for delivery are all based on this master timeline that you get from the gestational age.”
— Passage quoted in the Google Research post; speaker not named